- Home
- Common Shoulder Problems
- Supraspinatus Tendonitis
Supraspinatus Tendonitis
How To Beat Your Shoulder Pain
Written By: Chloe Wilson BSc (Hons) Physiotherapy
Reviewed By: SPE Medical Review Board

Supraspinatus tendonitis is a common shoulder problem, also referred to as “Painful Arc Syndrome”.
Supraspinatus symptoms may come on suddenly after an injury, or build-up gradually on and off over years with no obvious cause.
The classic sign of supraspinatus tendonitis is a painful arc when moving the arm out to the side, between 60-120 degrees of abduction as the tendon gets squashed against the bone in that range.
Symptoms of painful arc syndrome typically begin in middle-age, most frequently between the ages of 45-65.
Typically, supraspinatus tendonitis is an overuse injury caused by repetitive friction on the tendon, but it can be caused by a shoulder injury, instability or shoulder impingement.
Here we will look at:
- What Is Going On: a quick look at shoulder anatomy and how the tendon gets damaged
- Common Causes: what activities can lead to supraspinatus tendonitis
- Common Symptoms: how it typically presents with what symptoms
- Diagnosis: how the condition is accurately diagnosed and when to see a doctor
- Treatment: best ways to treat the tendonitis
- What Else Could It Be: how to tell if it's something else
What Is Going On?
Supraspinatus tendonitis is a common cause of shoulder pain. The shoulder joint is a ball a socket joint formed between the:
- Head of Humerus: the round head at the top of the upper arm bone
- Glenoid Fossa: the shallow socket on the lateral angle of the scapula (shoulder blade).
The shoulder is the most mobile joint in the whole body. Most joints get their stability from their bone structure but the shoulder sacrifices bony stability for mobility.
Think how much more movement you can do with your arms than your legs. But the huge range of motion at the shoulder puts it at much greater risk of injury.
To compensate, four muscles, known collectively as the rotator cuff, work together as the key dynamic stabilising muscles of the shoulder – supraspinatus, infraspinatus, teres minor and subscapularis.
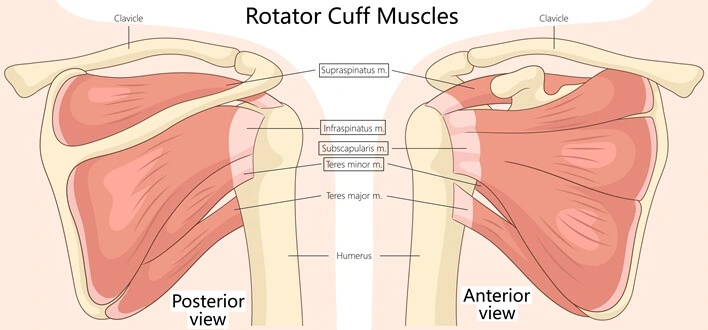
Supraspinatus lies across the top of the shoulder blade. The supraspinatus tendon passes through a narrow channel between the acromion and the head of the humerus, known as the “sub acromial space”.
The subacromial space is only around 7-14mm deep and is tightly packed with the:

- Supraspinatus Tendon
- Subacromial Bursa: a fluid filled sac that helps reduce friction through the subacromial space
- Joint Capsule: the upper part of the sac that surrounds the joint
- Long Head of Biceps Tendon
The space narrows considerably when the arm is raised around shoulder height, particularly when internally rotated (thumb pointing down).
The space then opens back up once the arm is raised higher and externally rotated (thumb pointing up).
What Causes Supraspinatus Tendonitis?
Supraspinatus tendonitis develops when there is repetitive friction on the tendon or it is repeatedly squashed or “impinged” in the subacromial space. This leads to inflammation and gradual degeneration of the tendon. It is extremely common affect 1-in-5 of adults.
In time, tears may also develop in the supraspinatus tendon leading to a partial or complete rotator cuff tear.
Common causes of painful arc syndrome include:
- Repetitive Overhead Activities: activities where your arm is frequently raised, such as sports e.g. tennis and swimming, and gardening e.g. hedge trimming or pruning
- Heavy Work: Repetitive heavy lifting overhead e.g. builders and labourers
- Posture: spending long periods slouched forwards reduces the subacromial space
- Genetic Predisposition: hereditary link
- Injury: e.g. fall on to an outstretched hand
- Age: The subacromial space tends to narrow with age due to wear and tear
- Primary Shoulder Impingement: Bone spurs or abnormal acromion position/shape reduce the subacromial space
- Secondary Shoulder Impingement: Dynamic shoulder instability – weakness in the rotator cuff muscles leads to poor control and thus friction
Supraspinatus Tendonitis may develop in isolation but it is often associated with other shoulder problems, particularly:
There is a lot of overlap in symptoms and treatments for these associated injuries but it is always worth finding out more about them.
Symptoms of Painful Arc Syndrome
Initially supraspinatus tendonitis pain is usually only experienced with repetitive or sustained overhead or reaching activities. However, over time, as the condition progresses, shoulder and arm pain at rest, weakness and stiffness can start to limit function.
Common symptoms of painful arc syndrome include:
- Shoulder Pain: A deep aching, burning pain at the top/front of the shoulder and outer arm at rest - may radiate down the upper arm but rarely to the elbow. Sharp, catching pain when twisting, reaching up or moving the arm out to the side

- Painful Arc: The classic feature is a painful arc where there is intense pain between 60-120o of shoulder abduction (lifting the arm out to the side), but outside this range movement is often pain-free
- Shoulder And Arm Weakness: Considerable weakness or weakness with no pain indicates a supraspinatus tendon full thickness tear
- Functional Limitation: Any activities at or above shoulder height may be painful and restricted e.g. reaching up to a cupboard, hanging up washing and washing/brushing your hair
- Sleep Disturbance: night pain is common with supraspinatus tendonitis, especially when lying on the affected side
- Full PROM: Whilst pain may limit active shoulder movement, passive movement (where the arm is moved by someone else so your muscles are completely relaxed) is typically full or nearly full with pure supraspinatus tendonitis as long as there are no other shoulder impingement problems
Diagnosing Supraspinatus Injuries
Supraspinatus tendonitis can usually be diagnosed by your doctor or physical therapist by talking to you about your symptoms and examining your shoulder.
If a partial or full thickness tear of the supraspinatus tendon is suspected, you may also be sent for an MRI or ultrasound scan.
Typical tests that are used to diagnose supraspinatus tendonitis are:

- Hawkins Kennedy Test
Position: Arm supported in 90o shoulder and elbow flexion
Test: Forearm pushed downwards to internally rotate shoulder. Test is repeated bringing arm into different positions of adduction across the body
Positive Result: Pain in the shoulder - Empty Can Test aka Jobe’s Test
Position: Both arms raised to 90 degrees abduction and 30 degrees forwards flexion, thumbs pointing to ceiling
Test: Rotate arms so thumbs pointing down. Examiner pushes down through forearms while patient resists the movement
Positive Result: Pain in the shoulder
If no pain is reported with either of these tests, then supraspinatus tendonitis is most likely not the problem.
When To See Your Doctor
Any new incidence of moderate to severe shoulder pain should be checked out by your doctor. Make a routine appointment it:
- It doesn't improve after 2-4 weeks of self-care
- The pain is getting progressively worse or disrupting your sleep
- Daily activities are affected by pain or limited range of motion
- Your shoulder feels weak, loose or unstable
Seek urgent medical care if:
- There is an obvious deformity
- Pain caused by a traumatic fall or severe injury
- Inability to move your shoulder/arm
- Persistent numbness or tingling in your arm
- Associated chest pain or shortness of breath
Treating Supraspinatus Tendonitis
The best treatments for supraspinatus tendonitis are:
1. Appropriate Rest
With supraspinatus tendonitis is really important to avoid activities which bring on your shoulder pain to reduce the stress on the tendon and give it time to heal. Failure to do so increases the risk of progression to a supraspinatus tendon full thickness tear.
2. Modify Sport Techniques
If your painful arc syndrome is linked to sport, seek expert advice on how to improve your technique to reduce the strain through the rotator cuff to prevent further irritation and supraspinatus tendon damage.
3. Medication
Painkillers e.g. paracetamol/Tylenol and anti-inflammatories e.g. ibuprofen/Advil tablets or gels can help reduce pain and inflammation with painful arc syndrome. Some people find a heat pack helps reduce the pain.
4. Ice-Cube Massage
Massaging a wet ice-cube over the tender area of the tendon for 10 minutes can help reduce localised pain and inflammation. Or simply place a shoulder ice pack over the affected area - there are some really great ones that strap to the shoulder so you can move around while wearing them, but stick to 10-15 minutes at a time.
5. Deep Transverse Friction Massage (DTFM)
Transverse frictions are a specific type of connective tissue massage delivered transversely across the tendon fibres. When done correctly, deep transverse friction massage helps to reduce pain and inflammation with supraspinatus tendonitis, speed up healing of the damaged tendon and improve function by:
- Hyperaemia: Increasing local blood flow to the area
- Local Heat Effect: raising the local temperature
- Removing Chemical Irritants: which would otherwise sensitize local nociceptors so pain receptors are less easily irritated
- Decrease Local Oedema: reducing swelling in the tendon
- Mobilise Adhesive Scar Tissue: helps to prevent the formation of adhesions and breaks down unwanted scar tissue and abnormal cross-fibres in the supraspinatus tendon. This helps to realign the damaged tendon fibres in the correct position and improves tensile strength
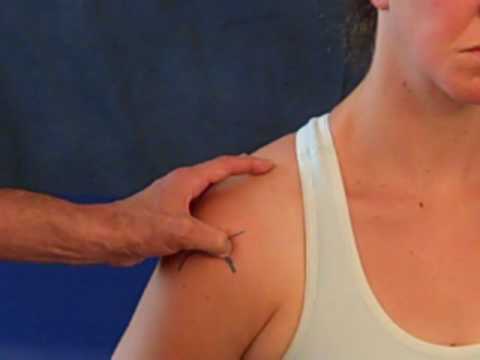
This helpful video from The Benjamin Institute shows the correct technique for deep transverse friction massage for supraspinatus tendonitis.
A common misconception is that Deep Transverse Friction Massage is painful, but when done correctly this is not the case.
Gentle pressure is used initially across the supraspinatus tendon until the area becomes numb, known as the analgesic effect. At this point the depth of pressure is gradually increased without inducing pain. The length and frequency of treatment will depend on the stage of injury.
Transverse friction massage should only be carried out by a trained professional such as a physical therapist as success relies on a good knowledge of anatomy and structural organisation of the tissue so that they can be applied to the exact site of the supraspinatus tendonitis lesions, in the correct direction and at the right depth for the appropriate duration and frequency.
6. Physical Therapy
Anyone suffering from painful arc syndrome should see a physical therapist. They will fully assess your shoulder and identify anything which may be contributing to your shoulder problem.
Physical therapy for supraspinatus tendonitis will usually involve a range of exercises to help strengthen and stabilise the shoulder as well as improve mobility:
- Scapular Stabilization Exercises: improves scapular control
- Rotator Cuff Exercises: improves shoulder strength
- Shoulder Stretches: reduce the tension through the muscles
- Upper Back Stretches: reduce pain and stiffness
Improving your posture can also make a massive difference.
Your physio may also use ultrasound treatment to help reduce inflammation and realign tendon fibres as is usually given 2-3 times a week for around 6 weeks.
7. Corticosteroid Injections
An injection of steroid and local anaesthetic can help to reduce pain and inflammation and aid healing with supraspinatus tendonitis.
Steroid injections do temporarily weaken the tendon and can temporarily increase shoulder pain so it is important to take things easy for a few days and avoid any heavy lifting. You shouldn’t have more than three shoulder injections per year.
8. Shoulder Surgery

Less than one quarter of patients will require surgery for supraspinatus tendonitis, even if there is a full thickness tear in the tendon.
But if the symptoms of supraspinatus tendonitis have failed to resolve after 3-6 months of conservative treatment, then shoulder surgery may be recommended.
This tends to be when there are other pathologies alongside supraspinatus tendonitis such as subacromial bursitis, bone spurs and/or rotator cuff tears.
Subacromial decompression surgery is the most common option to open up the subacromial space and is combined with a rotator cuff repair if the supraspinatus tendon is torn.
What Else Could It Be?
The two most classic indicators of supraspinatus tendonitis are a painful arc with shoulder abduction and tenderness when you press on the tendon.
If you don't have these symptoms, chances are it's not supraspinatus tendonitis, so check out the shoulder pain diagnosis section for help working out what is wrong.
Whilst supraspinatus tendonitis is one of the most common shoulder complaints, there are a number of other conditions that present in a similar way or that often go hand in hand with painful arc syndrome. These include:
- Shoulder Impingement Syndrome
- Subacromial Bursitis
- Rotator Cuff Tear
- Adhesive Capsulitis aka Frozen Shoulder
- Bicipital Tendonitis
- Shoulder Cysts
- Glenohumeral arthritis
- AC Arthritis
- Calcific tendonitis
These shoulder conditions may occur alongside supraspinatus tendonitis or on their own.
Related Articles

Medical & Scientific References
- Supraspinatus Tendonitis. National Library Of Medicine
- Supraspinatus Tendon Pathomechanics: A Current Concepts Review. International Journal Of Sports Physical Therapy
- Do therapeutic exercises impact supraspinatus tendon thickness? Secondary analyses of the combined dataset from two randomized controlled trials in patients with rotator cuff-related shoulder pain. Journal Of Shoulder & Elbow Surgery
Page Last Updated: September 23rd, 2026
Next Review Due: September 23rd, 2028

Visitor Comments
"Such an informative and valuable site. Clearly written and matches the guidance from my orthopedic surgeon. Even offers many rehab exercises. Thank you very much!" Izabela
"I am a massage therapist and found your website perfect. Very useful. Clear, easy understand. Big help. Thank you!" Viktoria
"This is a great site. Very informative" Marilyn
"I benefited a lot from your distinguished work, thank you." Sayed
"Hi
and thanks so much, great site! You
are doing a lot of good in the world with this helpful site, thanks again." Karen
The material on this website is intended for educational information purposes only. It should not delay or substitute medical advice, diagnosis or treatment. See our T&C's
Shoulder-Pain-Explained.com is a trading name of Wilson Health Ltd. All rights reserved. Terms & Conditions apply
© shoulder-pain-explained.com 2015-26 Last updated 15th June 2026
Contact Us About Us Blog Privacy Policy Advertising Policy Sitemap
